People search for a separated abdominal wall because they can see it. This page does not try to be the general explanation of that finding. Diastasis recti surgery is a narrower question: when a surgeon considers muscle repair, when they do not, and how that repair relates to a tummy tuck. The short description below is only enough to make the decision readable.
Plication itself, the stitch that narrows the gap, is explained on the muscle repair page. Men who have been left out of pregnancy-centred explanations should use diastasis recti in men. Both sit under the same limit: this section does not turn the finding into a measurement you can treat from an article.
What the condition is
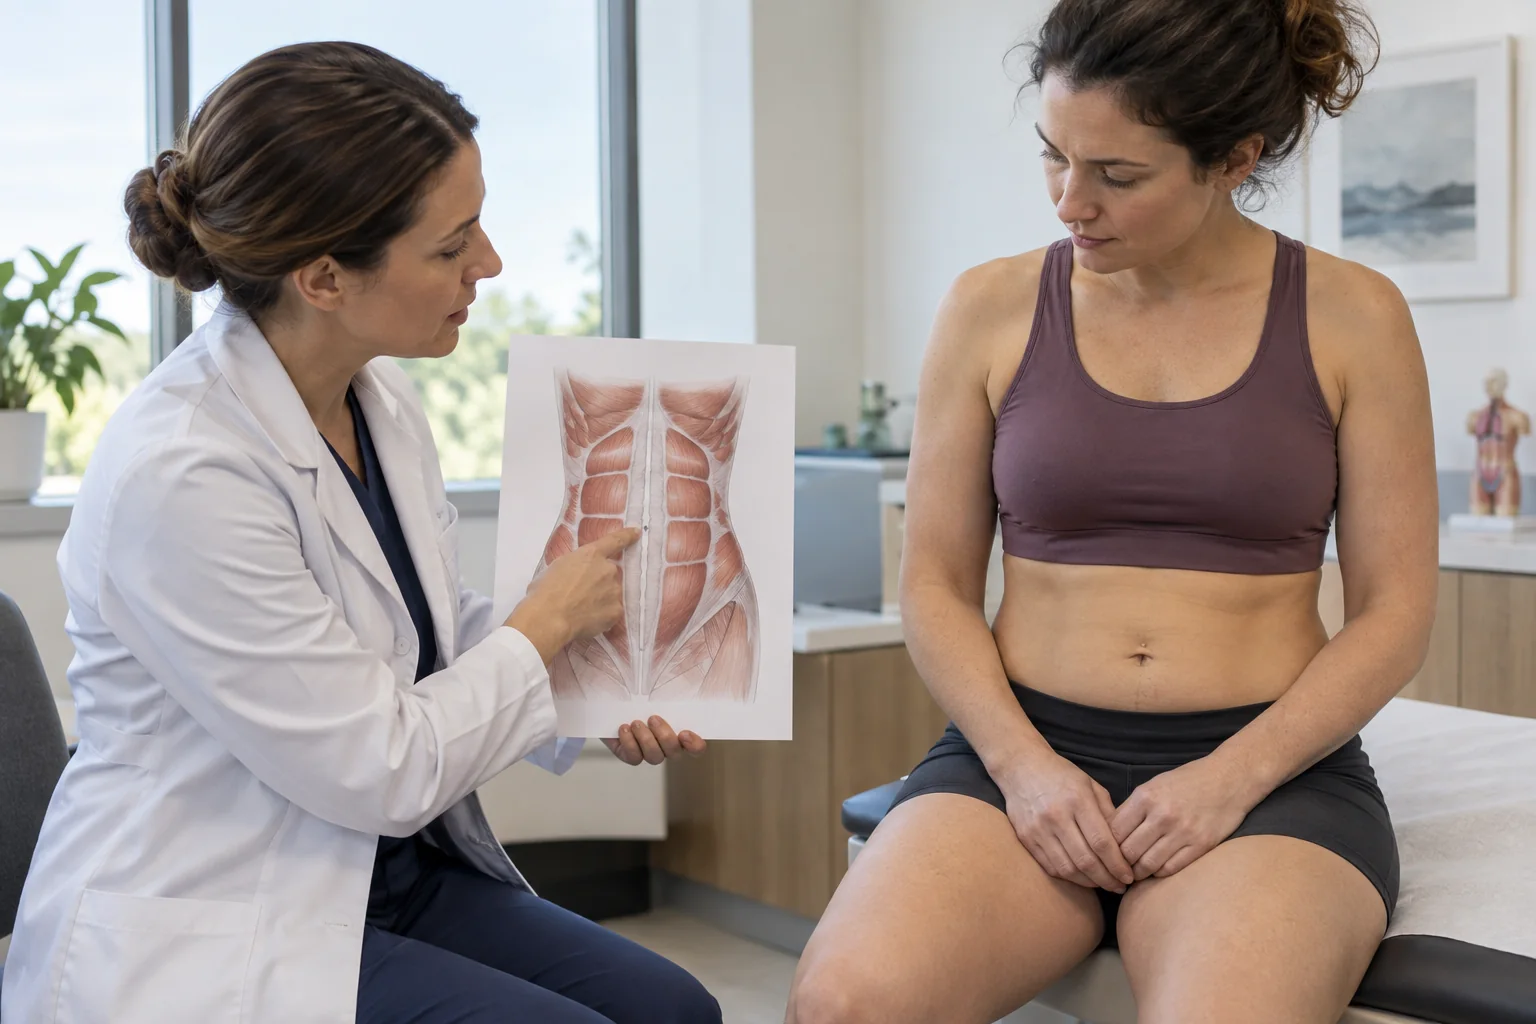
The rectus muscles run side by side down the front of the abdomen. Between them is a strip of connective tissue. When that strip stretches, the muscles sit further apart. Clinicians call the widening a diastasis. You may notice a ridge when you sit up, or a softness in the midline when you press.
That is the whole description this page needs. A diastasis is not assumed to be a hernia. A hernia is a defect that tissue can push through. The two can look similar, and only an examination separates them. If a lump appears when you cough or strain, that is a reason to be seen, not a reason to decide for yourself which name it has.
How severity is assessed
Severity is a clinical judgement. The examiner feels the gap with you lying down and as you lift your head, looks at the skin, and checks for a cough impulse that would suggest a hernia. Earlier operations, pregnancies, and large changes in weight belong in the history because they change what the wall has been through. They do not, by themselves, grade the gap.
You will see finger-breadths and centimetres quoted elsewhere. This page does not adopt a number. The sources used here do not give a width at which diastasis repair becomes the correct operation, and a borrowed cut-off would pretend to be a rule. Two people with the same measurement can be offered different plans once skin, symptoms, and risk are in the room.
Bring a list of medicines, say if you smoke, and say if you have had a clot in the leg or the lung. Say if you may become pregnant later. A later pregnancy can stretch a repair. This page does not cite a study of how often that happens, so it does not describe a percentage. It does say you should tell the surgeon before you book, not afterwards.
When surgery is considered — and when it is not
Diastasis recti surgery is considered when the clinician judges that the gap is part of a problem an operation can properly address, and that the risks are acceptable for you. Sometimes the problem is the contour of the midline together with loose skin. Sometimes it is a functional complaint, such as difficulty with the abdominal wall during ordinary movement, which still has to be assessed rather than taken from a form. Sometimes the honest outcome of the visit is that surgery is not what you need.
Surgery is not the next step in several ordinary situations. You have not been examined. Your weight is still moving. You smoke and stopping has not been discussed. You have a history of venous thromboembolism and no plan for how that would be handled around an operation. You cannot name who will review the wound. You want a guarantee about clothing size. None of these is a rebuke. Each is a reason to pause.
An operation also carries complications that have nothing to do with how reasonable the request feels. A review of abdominoplasty reported local complications in about 10% to 20% of patients and systemic complications in fewer than 1%2. Use that range as a description of tummy tuck surgery in the studies reviewed, not as the rate of diastasis repair done on its own. This page will not invent a cleaner number for the smaller operation.
| More likely to be discussed | A reason to wait |
|---|---|
| The abdominal wall has been examined, including for hernia | The decision is based on a photograph or a description |
| Skin, symptoms, and the gap have been separated in the plan | Weight is still changing, or smoking has not been addressed |
| You can name who reviews the wound afterwards | A history of clots has no plan attached |
| You know whether skin will be removed | You are being offered a result in a dress size |
Repair as part of a tummy tuck vs on its own
StatPearls describes abdominoplasty as removal of excess skin and subcutaneous fat with muscle tightening when indicated1. That is repair as part of a tummy tuck: the skin operation, plus plication because the surgeon has decided the midline is part of the indication. A traditional tummy tuck also moves the umbilicus1. A mini operation uses a shorter, lower incision and does not reposition the umbilicus1. Whether either of those includes plication is not settled by the length of the scar. Ask.
Repair on its own means the midline is tightened without that skin excision. It can be the right discussion when the skin is not the problem. It will disappoint you if loose skin is what you see, because tightening muscle does not take an apron away. The scar, the time in theatre, and the recovery are not interchangeable with a full abdominoplasty. This page does not describe a particular standalone technique, because the chapter it relies on is about abdominoplasty.
The sentence to take home is simple. One plan removes skin and may plicate. The other plicates and does not remove that skin. What the operation involves covers the skin side. If those two sentences are not in your quote, you are not ready to choose between them.
Recovery implications
After plication the abdominal wall is tighter. Bending slightly at the hips is often more comfortable at first, and pulling straight up can tug on the repair. How many days that lasts is your surgeon's instruction, not a figure this page will guess. Drains are commonly one or two, and not mandatory1. Whether you have them depends on the operation you actually had.
The early course of a tummy tuck, including when to call for help, is on the recovery pages. Contact your GP or NHS 111 for a wound concern, a temperature, or a swelling that is new and one-sided. Call 999 for sudden breathlessness, chest pain, or bleeding that will not stop. Those signs are not a normal "tight" feeling from the repair.
A repair does not look after itself. Someone has to see the wound. If that person is not the surgeon who operated, agree who it is before the day, not on the day you are worried.
NHS position
The NHS position on diastasis repair is not a paragraph this page can honestly copy. Cosmetic abdominoplasty is a different request from care for a functional problem, and integrated care boards do not all use the same wording. Read the NHS page for how funding is approached. Do not treat a forum post, or a private clinic's screen, as the policy.
If you are told the operation is cosmetic, that is a funding category, not a comment on whether the gap is real. If you are told it might be considered for a functional reason, that is still an application, not an approval. This page will not upgrade either sentence into a promise.
Cost
The fee method for this site, including repair, is on the fee guide's diastasis section. This page does not repeat a figure. What you should still check on any quote is whether muscle tightening is inside the price you were shown or listed as a later extra. A headline that says "tummy tuck" and never mentions the muscles has not answered the question this page is about.
Frequently asked questions
-
When is diastasis recti surgery considered?
Surgery is considered after a clinician has examined the abdominal wall and judges that muscle repair fits the problem, sometimes together with removal of skin. A gap you can see is a reason to be assessed, not an instruction to book. This page does not print a width at which an operation starts. The muscle repair page explains what plication is.
-
When is surgery not the right next step?
It is the wrong next step when you have not been examined, when your weight is still changing quickly, when you smoke and have not discussed stopping, or when nobody has a plan for the wound afterwards. A wish to change shape is not, on its own, an indication. The NHS page is where funding questions belong, and they are separate from this judgement.
-
Is repair the same operation as a tummy tuck?
No. A tummy tuck removes excess skin and can tighten muscle when that is indicated. Diastasis repair is the muscle step. It may be included in a tummy tuck, or discussed without skin removal. They produce different scars and different recoveries. Ask which one is written in the plan before you compare them.
-
Does a mini tummy tuck include muscle repair?
Not as a rule this page will invent. A mini operation uses a shorter, lower incision and does not reposition the umbilicus. Whether the midline is plicated is a separate question, and the surgeon has to answer it for your abdomen. Read what the operation involves before you assume a short scar means the muscles were tightened.
-
Will the NHS pay for diastasis repair?
This page does not say yes or no. Cosmetic abdominoplasty and a functional problem are different requests, and local decisions are not copied here. Use the NHS page for that question. Do not treat a private quote as evidence of what the NHS will fund.
-
Where is the cost of repair explained?
On the fee guide, in the diastasis section. This page does not repeat a figure. A quote should say whether muscle tightening is included or billed as an extra step. If the sentence is missing, you are not yet comparing like with like.